

Support Chiropractic Research!

BLOG

A Diagnosis-based Clinical Decision Rule For Spinal Pain Part 2: Review Of The Literature

By |January 13, 2014|Chiropractic Education, Clinical Decision-making, Diagnosis, Spinal Manipulation|

A Diagnosis-based Clinical Decision Rule For Spinal Pain Part 2: Review Of The Literature

The Chiro.Org Blog


SOURCE:   Chiropractic & Osteopathy 2008 (Aug 11); 16: 7


Donald R Murphy, Eric L Hurwitz, and Craig F Nelson

Rhode Island Spine Center,
Pawtucket, RI 02860, USA


BACKGROUND:   Spinal pain is a common and often disabling problem. The research on various treatments for spinal pain has, for the most part, suggested that while several interventions have demonstrated mild to moderate short-term benefit, no single treatment has a major impact on either pain or disability. There is great need for more accurate diagnosis in patients with spinal pain. In a previous paper, the theoretical model of a diagnosis-based clinical decision rule was presented. The approach is designed to provide the clinician with a strategy for arriving at a specific working diagnosis from which treatment decisions can be made. It is based on three questions of diagnosis. In the current paper, the literature on the reliability and validity of the assessment procedures that are included in the diagnosis-based clinical decision rule is presented.

METHODS:   The databases of Medline, Cinahl, Embase and MANTIS were searched for studies that evaluated the reliability and validity of clinic-based diagnostic procedures for patients with spinal pain that have relevance for questions 2 (which investigates characteristics of the pain source) and 3 (which investigates perpetuating factors of the pain experience). In addition, the reference list of identified papers and authors’ libraries were searched.

RESULTS:   A total of 1769 articles were retrieved, of which 138 were deemed relevant. Fifty-one studies related to reliability and 76 related to validity. One study evaluated both reliability and validity.

CONCLUSION:   Regarding some aspects of the DBCDR, there are a number of studies that allow the clinician to have a reasonable degree of confidence in his or her findings. This is particularly true for centralization signs, neurodynamic signs and psychological perpetuating factors. There are other aspects of the DBCDR in which a lesser degree of confidence is warranted, and in which further research is needed.


From the FULL TEXT Article:

Introduction

Accurate diagnosis or classification of patients with spinal pain has been identified as a research priority [1]. We presented in Part 1 the theoretical model of an approach to diagnosis in patients with spinal pain [2]. This approach incorporated the various factors that have been found, or in some cases theorized, to be of importance in the generation and perpetuation of neck or back pain into an organized scheme upon which a management strategy can be based. The authors termed this approach a diagnosis-based clinical decision rule (DBCDR). The DBCDR is not a clinical prediction rule. It is an attempt to identify aspects of the clinical picture in each patient that are relevant to the perpetuation of pain and disability so that these factors can be addressed with interventions designed to improve them. The purpose of this paper is to review the literature on the methods involved in the DBCDR regarding reliability and validity and to identify those areas in which the literature is currently lacking.

The Three Essential Questions of Diagnosis

The DBCDR is based on what the authors refer to as the 3 essential questions of diagnosis [2]. The answers to these questions supply the clinician with the most important information that is required to develop an individualized diagnosis from which a management strategy can be derived.

There are more articles like this @ our:

Low Back Pain Page and the:
Chronic Neck Pain and Chiropractic Page and the:

Clinical Model for the Diagnosis and Management Page

(more…)

A Theoretical Model For The Development Of A Diagnosis-based Clinical Decision Rule For The Management Of Patients With Spinal Pain

By |January 12, 2014|Chiropractic Care, Clinical Decision-making, Diagnosis, Evidence-based Medicine|

A Theoretical Model For The Development Of A Diagnosis-based Clinical Decision Rule For The Management Of Patients With Spinal Pain

The Chiro.Org Blog


BMC Musculoskelet Disord. 2007 (Aug 3); 8: 75 ~ FULL TEXT


Donald R Murphy and Eric L Hurwitz

Rhode Island Spine Center,
Pawtucket, RI, USA.
rispine@aol.com


BACKGROUND:   Spinal pain is a common problem, and disability related to spinal pain has great consequence in terms of human suffering, medical costs and costs to society. The traditional approach to the non-surgical management of patients with spinal pain, as well as to research in spinal pain, has been such that the type of treatment any given patient receives is determined more by what type of practitioner he or she sees, rather than by diagnosis. Furthermore, determination of treatment depends more on the type of practitioner than by the needs of the patient. Much needed is an approach to clinical management and research that allows clinicians to base treatment decisions on a reliable and valid diagnostic strategy leading to treatment choices that result in demonstrable outcomes in terms of pain relief and functional improvement. The challenges of diagnosis in patients with spinal pain, however, are that spinal pain is often multifactorial, the factors involved are wide ranging, and for most of these factors there exist no definitive objective tests.

DISCUSSION:   The theoretical model of a diagnosis-based clinical decision rule has been developed that may provide clinicians with an approach to non-surgical spine pain patients that allows for specific treatment decisions based on a specific diagnosis. This is not a classification scheme, but a thought process that attempts to identify most important features present in each individual patient. Presented here is a description of the proposed approach, in which reliable and valid assessment procedures are used to arrive at a working diagnosis which considers the disparate factors contributing to spinal pain. Treatment decisions are based on the diagnosis and the outcome of treatment can be measured.

SUMMARY:   In this paper, the theoretical model of a proposed diagnosis-based clinical decision rule is presented. In a subsequent manuscript, the current evidence for the approach will be systematically reviewed, and we will present a research strategy required to fill in the gaps in the current evidence, as well as to investigate the decision rule as a whole.


From the FULL TEXT Article:

Introduction

Chronic spinal pain is an increasingly common problem in Western Society [1]. Spinal disorders exact great costs, in terms of both direct medical costs and indirect costs related to disability and lost productivity [1-3]. A number of researchers have attempted to improve our ability to identify the causes of spinal pain as well as to diagnose and treat patients with this problem. In spite of this, accurate diagnosis, leading to specific, targeted treatments, of patients with spinal pain has been elusive.

It has been repeated over the years that only in 15% of patients with spinal pain can a definitive diagnosis be made [4-6]. However, if one surveys the spine literature, one finds a variety of methods for detecting many of the factors that are believed to be of importance, most of which have known reliability and validity, although there are some that do not. Each of these methods may only help the clinician to identify one particular potential contributing factor in the overall clinical picture of the spine pain patient. However, it may be possible that, by utilizing many of the various diagnostic procedures available to the spine clinician, one can develop a specific working diagnosis that encompasses all of the dimensions for which there may be contributing factors and from which a management strategy may be designed that addresses each of the most important factors in each individual patient.

There are more articles like this @ our:

Low Back Pain Page and the:

Chronic Neck Pain and Chiropractic Page and the:

Clinical Model for the Diagnosis and Management Page

(more…)

Southern California University of Health Sciences Selected for the Department of Veterans Affairs’ First-Ever Chiropractic Residency Program

By |January 8, 2014|Education|

Source PR NewsWire

WHITTIER, Calif., Jan. 6, 2014 /PRNewswire/ — Southern California University of Health Sciences (SCUHS) is proud to announce its participation in the first ever VA chiropractic residency training program. On December 6, 2013, the Department of Veterans Affairs (VA) unveiled its plan to initiate a pioneering chiropractic residency program beginning in July, 2014.

The focus of each VA residency program is Integrated Clinical Practice, with training that will emphasize the provision of chiropractic care as an important part of an integrated healthcare system. These hospital-based training programs will also expand each resident’s ability to collaborate with other healthcare professionals through interdisciplinary rotations. Residents will develop their knowledge of hospital practice, policies and procedures, and will be better prepared for future positions in VA, other healthcare systems, and/or academic settings.

After a highly competitive application process, only five VA medical centers and four academic affiliates were chosen nationwide to pilot this program. Several competing VA medical centers and academic institutions attempted to earn this distinction and as one of the four chosen academic affiliates, Southern California University is honored to partner with the well-known and well-respected VA Greater Los Angeles Healthcare System (VAGLAHS).

“To our delight, today’s healthcare environment continues to moves towards interdisciplinary practice and team care,” said Dr.Melissa Nagare Kimura, Chief Clinical Officer and Associate Vice President for SCU Health System. “SCU prides itself in cultivating an environment of evidence-informed inter-professional education and practice, and this is just one reason why the university is thrilled to be a part of such an innovative program.”

This new residency will provide advanced clinical training in complex case management, allowing recent chiropractic graduates to increase their scope and depth of clinical knowledge, experience and acumen. Residents will be mentored by senior VA chiropractors who are national leaders in integrated chiropractic practice. These clinicians will share their expertise in patient care, academics and research to provide a robust educational experience.

According to Dr. John Scaringe, President of Southern California University of Health Sciences, “This is not only exciting news for SCU, but also for chiropractic doctors and students nationwide. This opportunity, created by the Department of Veterans Affairs, shows that the VA embraces chiropractic as a specialty and should be viewed as a pioneering effort. Everyone at SCU could not be more pleased to be a part of this program launch and could not be more honored to be working as the academic affiliate for the distinguished VA Greater Los Angeles Health Care System.”

ABOUT VA CHIROPRACTIC RESIDENCY PROGRAMS
The programs will be administered nationally by VA’s Office of Academic Affiliations and locally by each individual participating VA facility. Each VA facility partners with its affiliated Council on Chiropractic Education (CCE) accredited chiropractic school in conducting the program.

Sleep Characteristics in Patients with Whiplash-Associated Disorders: A Descriptive Study

By |January 7, 2014|Chiropractic Care, Whiplash|

Sleep Characteristics in Patients with Whiplash-Associated Disorders: A Descriptive Study

The Chiro.Org Blog


SOURCE:   Topics in Integrative Health Care 2012 (Dec 31); 3 (4)


Jay Greenstein, DC, CCSP, CGFI-L, CKTP, FMS; Barton Bishop, DPT, SCS, CKTI, TPI, CGFI-MP, CSCS; Jean Edward, RN, BSN; Allen Huffman, DC, CKTP, BS; Danielle Davis; Robert Topp, RN, PhD


Study Objectives:   The purpose of this study was to explore sleep habits and characteristics of patients with whiplash-associated disorders (WAD) presenting at an outpatient, chiropractic clinic using the Medical Outcomes Study (MOS) Sleep Scale.

Methods:   Fifty-one patients from an outpatient chiropractic and physical therapy clinic specializing in spinal rehabilitation participated in this cross-sectional, descriptive study. Data were collected using a descriptive survey, the Visual Analog Scale (VAS), the Neck Disability Index (NDI), and the self-administered 12-item MOS Sleep Scale. Data analysis included descriptive statistics to describe pain, disability, and sleep characteristics of the study sample, and computation of confidence intervals to determine differences in means of sleep characteristics between the non-WAD population (as determined by previous studies) and the study sample of WAD patients.

Results:   Results indicate that when compared to normative values of the non-WAD population, the sample of WAD patients in this study presents with significantly greater measures of neck disability (NDI), neck pain (VAS), sleep disturbance, snoring, shortness of breath and headache, sleep somnolence and sleep problems index I and II. This sample also presents with significantly lower measures of optimal sleep when compared to the general population.

Conclusion:   Consistent with previous research, findings from this study indicate that WAD patients have increased neck disability and pain, and poorer sleep outcomes, indicating the need for clinicians to assess sleep characteristics and incorporate interventions aimed at alleviating these symptoms when planning rehabilitation. Findings provide evidence for the need to further explore sleep disturbances among WAD patients to establish a stronger understanding of the course and prognosis of this condition.


From the FULL TEXT Article:

Introduction

Neck pain related to whiplash-associated disorders (WAD) constitutes a significant health issue that leads patients to seek medical care in chiropractic and other physical therapy, rehabilitative clinics. Studies have indicated that individuals experience multiple clinical manifestations of WADs that lead to chronicity including postural changes, disability, headache, fatigue, and sleep disturbances. [1-4] Although studies have shown that sleep disturbances occur as a result of chronic pain, few studies have explored the relationship between patients with WAD and sleep quality. [4-6]

There are many more articles like this @ our:

The Whiplash Page and the

Chronic Neck Pain and Chiropractic Page

(more…)

Epidural Steroid Injections: Are long-term Risks Worth Short Term Benefits?

By |January 5, 2014|Iatrogenic Injury, Steroids|

Epidural Steroid Injections: Are long-term Risks Worth Short Term Benefits?

The Chiro.Org Blog


SOURCE:   ACA News ~ February 2014

By William Morgan, DC


Outpatient procedures are where the money is in medicine these days. Such procedures are invasive treatments that are not quite surgery but are not conservative care either. Non-surgical procedura lists are falling over themselves at an alarming rate to learn these lucrative businesses. This is true in several medical specialties: cardiac catheterization labs, GI endoscopies and colonoscopies, interventional radiology procedures, PMR pain procedures, urologic cystoscopies, chiropractic manipulation under anesthesia, epidural steroid injection therapies and many other pain procedures. If utilized correctly, these procedures may be valuable tools in the treatment of patients by preventing more invasive procedures, and in the case of cystoscopies and colonoscopies, aid in the early detection of cancer.

These procedures can be done quickly with assembly line efficiency and are very profitable for the physicians. In the case of epidural steroid injections (ESI), a ten-minute epidural procedure will generally yield anywhere from a couple hundred to a couple thousand dollars, though I have heard of a series of three epidurals going for as much as $8,000. Furthermore, if done in an outpatient facility, the physician does not have to split the fees with a hospital, and the insurance company does not need to pay the higher costs that normally accompany hospital-based procedures. Last year in the United States, the Centers for Medicare and Medicaid Services (CMS) paid for nearly nine million ESI. This number may not appear surprising at first, but when you consider that ESI therapies are neither approved by the FDA [1] nor recommended by the manufacturers [2] due to reports of severe adverse events, it becomes alarmingly relevant. Note that the CMS number is not the total number of ESI performed in the United States. The nine million number represents only those ESI paid for by CMS. When we add in the number of ESI performed in the DOD, VA, workers’ compensation systems and private insurance, that number could conceivably be in the tens of millions.

While it is true that ESI are not FDA approved, Medicare, Medicaid, workers’ compensation and most other insurers continue to pay hundreds of millions of dollars per year for this controversial procedure.

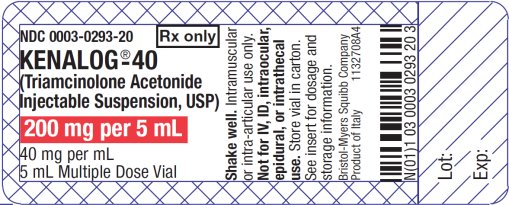
Ironically, on every vial of Kenalog (a popular steroid used for epidural injections) there is actually a warning against its use for epidural injections, yet proceduralists continue to use it.

There are more articles like this @ our:

The Iatrogenic Injury Page

(more…)

A Randomised Controlled Trial of Preventive Spinal Manipulation with and without a Home Exercise Program for Patients with Chronic Neck Pain

By |December 25, 2013|Chiropractic Care, Chronic Pain, Evidence-based Medicine|

A Randomised Controlled Trial of Preventive Spinal Manipulation with and without a Home Exercise Program for Patients with Chronic Neck Pain

The Chiro.Org Blog


SOURCE:   BMC Musculoskelet Disord. 2011 (Feb 8);   12:   41


Johanne Martel, Claude Dugas, Jean-Daniel Dubois, and Martin Descarreaux

Département de Chiropratique,
Université du Québec à Trois-Rivières,
Trois-Rivières G9A 5H7, Canada.


Background:   Evidence indicates that supervised home exercises, combined or not with manual therapy, can be beneficial for patients with non-specific chronic neck pain (NCNP). The objective of the study is to investigate the efficacy of preventive spinal manipulative therapy (SMT) compared to a no treatment group in NCNP patients. Another objective is to assess the efficacy of SMT with and without a home exercise program.

Methods:   Ninety-eight patients underwent a short symptomatic phase of treatment before being randomly allocated to either an attention-group (n = 29), a SMT group (n = 36) or a SMT + exercise group (n = 33). The preventive phase of treatment, which lasted for 10 months, consisted of meeting with a chiropractor every two months to evaluate and discuss symptoms (attention-control group), 1 monthly SMT session (SMT group) or 1 monthly SMT session combined with a home exercise program (SMT + exercise group). The primary and secondary outcome measures were represented by scores on a 10-cm visual analog scale (VAS), active cervical ranges of motion (cROM), the neck disability index (NDI) and the Bournemouth questionnaire (BQ). Exploratory outcome measures were scored on the Fear-avoidance Behaviour Questionnaire (FABQ) and the SF-12 Questionnaire.

Results:   Our results show that, in the preventive phase of the trial, all 3 groups showed primary and secondary outcomes scores similar to those obtain following the non-randomised, symptomatic phase. No group difference was observed for the primary, secondary and exploratory variables. Significant improvements in FABQ scores were noted in all groups during the preventive phase of the trial. However, no significant change in health related quality of life (HRQL) was associated with the preventive phase.

There are more articles like this @ our:

Chronic Neck Pain and Chiropractic Page and our

Maintenance Care, Wellness and Chiropractic Page

(more…)