

Support Chiropractic Research!

Frank M. Painter

About Frank M. Painter

I was introduced to Chiro.Org in early 1996, where my friend Joe Garolis helped me learn HTML, the "mark-up language" for websites. We have been fortunate that journals like JMPT have given us permission to reproduce some early important articles in Full-Text format. Maintaining the Org website has been, and remains, my favorite hobby.

Integration of Doctors of Chiropractic Into Private Sector Health Care

By |April 13, 2018|Integrative Care|

Integration of Doctors of Chiropractic Into Private Sector Health Care Facilities in the United States: A Descriptive Survey

The Chiro.Org Blog


SOURCE:   J Manipulative Physiol Ther. 2018 (Feb); 41 (2): 149–155


Stacie A. Salsbury, PhD, RN, Christine M. Goertz, DC, PhD, Elissa J. Twist, DC, MS, Anthony J. Lisi, DC

Palmer Center for Chiropractic Research,
Palmer College of Chiropractic,
Davenport, Iowa.

OBJECTIVE:   The purpose of this study was to describe the demographic, facility, and practice characteristics of doctors of chiropractic (DCs) working in private sector health care settings in the United States.

METHODS:   We conducted an online, cross-sectional survey using a purposive sample of DCs (n = 50) working in integrated health care facilities. The 36-item survey collected demographic, facility, chiropractic, and interdisciplinary practice characteristics, which were analyzed with descriptive statistics.

RESULTS:   The response rate was 76% (n = 38). Most respondents were men and mid-career professionals with a mean 21 years of experience in chiropractic. Doctors of chiropractic reported working in hospitals (40%), multispecialty offices (21%), ambulatory clinics (16%), or other (21%) health care settings. Most (68%) were employees and received salary compensation (59%). The median number of DCs per setting was 2 (range 1–8). Most DCs used the same health record as medical staff and worked in the same clinical setting. More than 60% reported co-management of patients with medical professionals. Integrated DCs most often received and made referrals to primary care, physical medicine, pain medicine, orthopedics, and physical or occupational therapy. Although in many facilities the DCs were exclusive providers of spinal manipulation (43%), in most, manipulative therapies also were delivered by physical therapists and osteopathic or medical physicians. Informal face-to-face consultations and shared health records were the most common communication methods.

There are more articles like this @ our:
Integrated Health Care and Chiropractic Page

(more…)

Spinal Manipulative Therapy and Other Conservative Treatments

By |April 12, 2018|Guidelines, Low Back Pain|

Spinal Manipulative Therapy and Other Conservative Treatments for Low Back Pain:
A Guideline From the Canadian Chiropractic Guideline Initiative

The Chiro.Org Blog


SOURCE:   J Manipulative Physiol Ther. 2018 (Mar 29) [Epub]


André E. Bussières, DC, FCCS(C), PhD, Gregory Stewart, DC, Fadi Al-Zoubi, PT, MSc, Philip Decina, DC, Martin Descarreaux, DC, PhD, Danielle Haskett, BSc, Cesar Hincapié, DC, PhD, Isabelle Pagé, DC, MSc, Steven Passmore, DC, PhD, John Srbely, DC, PhD, Maja Stupar, DC, PhD, Joel Weisberg, DC, Joseph Ornelas, DC, PhD

School of Physical and Occupational Therapy,
Faculty of Medicine, McGill University,
Montreal, Québec, Canada


OBJECTIVE: &nbsp The objective of this study was to develop a clinical practice guideline on the management of acute and chronic low back pain (LBP) in adults. The aim was to develop a guideline to provide best practice recommendations on the initial assessment and monitoring of people with low back pain and address the use of spinal manipulation therapy (SMT) compared with other commonly used conservative treatments.

METHODS: &nbsp The topic areas were chosen based on an Agency for Healthcare Research and Quality comparative effectiveness review, specific to spinal manipulation as a nonpharmacological intervention. The panel updated the search strategies in Medline. We assessed admissible systematic reviews and randomized controlled trials for each question using A Measurement Tool to Assess Systematic Reviews and Cochrane Back Review Group criteria. Evidence profiles were used to summarize judgments of the evidence quality and link recommendations to the supporting evidence. Using the Evidence to Decision Framework, the guideline panel determined the certainty of evidence and strength of the recommendations. Consensus was achieved using a modified Delphi technique. The guideline was peer reviewed by an 8-member multidisciplinary external committee.

RESULTS: &nbsp For patients with acute (0-3 months) back pain, we suggest offering advice (posture, staying active), reassurance, education and self-management strategies in addition to SMT, usual medical care when deemed beneficial, or a combination of SMT and usual medical care to improve pain and disability. For patients with chronic (>3 months) back pain, we suggest offering advice and education, SMT or SMT as part of a multimodal therapy (exercise, myofascial therapy or usual medical care when deemed beneficial). For patients with chronic back-related leg pain, we suggest offering advice and education along with SMT and home exercise (positioning and stabilization exercises).

There are more articles like this @ our:

Low Back Pain Guidelines Page

(more…)

Preferences for Web-Based Information Material for Low Back Pain

By |April 11, 2018|Patient Expectations|

Preferences for Web-Based Information Material for Low Back Pain:
Qualitative Interview Study on People Consulting a General Practitioner

The Chiro.Org Blog


SOURCE:   JMIR Rehabil Assist Technol. 2018 (Apr 2); 5 (1): e7


Allan Riis, PhD; Ditte Meulengracht Hjelmager, MSc; Line Dausel Vinther, MSc; Michael Skovdal Rathleff, PhD; Jan Hartvigsen, PhD; Martin Bach Jensen, MD, PhD

Research Unit for General Practice in Aalborg,
Department of Clinical Medicine,
Aalborg University,
Aalborg, Denmark.


BACKGROUND:   Information on self-management, including addressing people’s fears and concerns, are core aspects of managing patients with low back pain (LBP). Web apps with patient information may be used to extend patient-physician consultations and encourage self-management outside of the consultation room. It is, however, important to identify the end users’ needs and preferences in order to maximize acceptance.

OBJECTIVE:   The aim of this study was to identify preferences for the content, design, and functionality of a Web app with evidence-based information and advice for people with LBP in Denmark.

METHODS:   This is a phenomenological qualitative study. Adults who had consulted their general practitioner because of LBP within the past 14 days were included. Each participated in a semistructured interview, which was audiotaped and transcribed for text condensation. Interviews were conducted at the participant’s home by 2 interviewers. Participants also completed a questionnaire that requested information on age, gender, internet usage, interest in searching new knowledge, LBP-related function, and pain.

RESULTS:   Fifteen 45-min interviews were conducted. Participants had a median age of 40 years (range 22-68 years) and reported a median disability of 7 points (range 0-18) using the 23-item Roland Morris Disability Questionnaire. Participants reported that Web-based information should be easy to find and read, easily overviewed, and not be overloaded with information. Subjects found existing Web-based information confusing, often difficult to comprehend, and not relevant for them, and they questioned the motives driving most hosting companies or organizations. The Patient Handbook, a Danish government-funded website that provides information to Danes about health, was mentioned as a trustworthy and preferred site when searching for information and advice regarding LBP.

There are more articles like this @ our:
Low Back Pain and Chiropractic Page

(more…)

Prognostic Implications of the Quebec Task Force Classification

By |April 9, 2018|Low Back Pain, Sciatica|

Prognostic Implications of the Quebec Task Force Classification of Back-related Leg Pain:
An Analysis of Longitudinal Routine Clinical Data

The Chiro.Org Blog


SOURCE:   BMC Musculoskelet Disord. 2013 (May 24); 14: 171


Alice Kongsted, Peter Kent, Tue Secher Jensen, Hanne Albert and Claus Manniche

Research Department,
The Spine Centre of Southern Denmark,
Middelfart, Hospital Lillebaelt,
Institute of Regional Health Services Research,
University of Southern Denmark,
Middelfart, Denmark


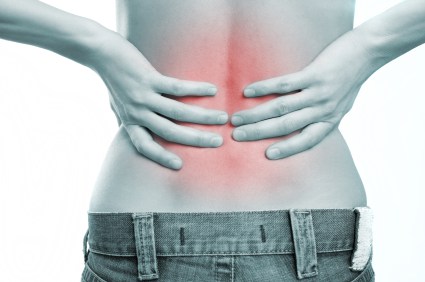
BACKGROUND:   Low back pain (LBP) patients with related leg pain have a more severe profile than those with local LBP and a worse prognosis. Pain location above or below the knee and the presence of neurological signs differentiate patients with different profiles, but knowledge about the prognostic value of these subgroups is sparse. The objectives of this study were (1) to investigate whether subgroups consisting of patients with Local LBP only, LBP + leg pain above the knee, LBP + leg pain below the knee, and LBP + leg pain and neurological signs had different prognoses, and (2) to determine if this was explained by measured baseline factors.

METHODS:   Routine clinical data were collected during the first visit to an outpatient department and follow-ups were performed after 3 and 12 months. Patients were divided into the four subgroups and associations between subgroups and the outcomes of activity limitation, global perceived effect (GPE) after 3 months, and sick leave after 3 months were tested by means of generalised estimating equations. Models were univariate (I), adjusted for duration (II), and adjusted for all baseline differences (III).

RESULTS:   A total of 1,752 patients were included, with a 76% 3-month and 70% 12-month follow-up. Subgroups were associated with activity limitation in all models (p < 0.001). Local LBP had the least and LBP + neurological signs the most severe limitations at all time-points, although patients with neurological signs improved the most. Associations with GPE after 3 months were only significant in Model I. Subgroups were associated with sick leave after 3 months in model I and II, with sick leave being most frequent in the subgroup with neurological signs. No significant differences were found in any pairwise comparisons of patients with leg pain above or below the knee.

There are more articles like this @ our:
Chiropractic and Sciatica Page and the:

Low Back Pain and Chiropractic Page

(more…)

What Low Back Pain Is and Why We Need to Pay Attention

By |April 7, 2018|Low Back Pain|

What Low Back Pain Is and Why We Need to Pay Attention

The Chiro.Org Blog


SOURCE:   Lancet. 2018 (Mar 20) [Epub]


Prof Jan Hartvigsen, PhD, Mark J Hancock, PhD, Alice Kongsted, PhD, Prof Quinette Louw, PhD, Manuela L Ferreira, PhD, Stéphane Genevay, MD, Damian Hoy, PhD, Prof Jaro Karppinen, PhD, Glenn Pransky, MD, Prof Joachim Sieper, MD, Prof Rob J Smeets, PhD, Prof Martin Underwood, MD

Department of Sports Science and Clinical Biomechanics,
University of Southern Denmark,
Odense, Denmark;
Nordic Institute of Chiropractic and Clinical Biomechanics,
Odense, Denmark.


Low back pain is a very common symptom. It occurs in high-income, middle-income, and low-income countries and all age groups from children to the elderly population. Globally, years lived with disability caused by low back pain increased by 54% between 1990 and 2015, mainly because of population increase and ageing, with the biggest increase seen in low-income and middle-income countries. Low back pain is now the leading cause of disability worldwide.

This is just one article from a series of 4:

The Lancet 2018 Series on Low Back Pain

For nearly all people with low back pain, it is not possible to identify a specific nociceptive cause. Only a small proportion of people have a well understood pathological cause – eg, a vertebral fracture, malignancy, or infection. People with physically demanding jobs, physical and mental comorbidities, smokers, and obese individuals are at greatest risk of reporting low back pain. Disabling low back pain is over-represented among people with low socioeconomic status. Most people with new episodes of low back pain recover quickly; however, recurrence is common and in a small proportion of people, low back pain becomes persistent and disabling.

Initial high pain intensity, psychological distress, and accompanying pain at multiple body sites increases the risk of persistent disabling low back pain. Increasing evidence shows that central pain-modulating mechanisms and pain cognitions have important roles in the development of persistent disabling low back pain. Cost, health-care use, and disability from low back pain vary substantially between countries and are influenced by local culture and social systems, as well as by beliefs about cause and effect.

Disability and costs attributed to low back pain are projected to increase in coming decades, in particular in low-income and middle-income countries, where health and other systems are often fragile and not equipped to cope with this growing burden. Intensified research efforts and global initiatives are clearly needed to address the burden of low back pain as a public health problem.


From the FULL TEXT Article:

Introduction

Low back pain is an extremely common symptom experienced by people of all ages. [1–3] In 2015, the global point prevalence of activity-limiting low back pain was 7.3%, implying that 540 million people were affected at any one time. Low back pain is now the number one cause of disability globally. [4] The largest increases in disability caused by low back pain in the past few decades have occurred in low-income and middle-income countries, including in Asia, Africa, and the Middle East, [5] where health and social systems are poorly equipped to deal with this growing burden in addition to other priorities such as infectious diseases.

There are more articles like this @ our:
Low Back Pain and Chiropractic Page

(more…)

Prevention and Treatment of Low Back Pain

By |April 6, 2018|Low Back Pain|

Prevention and Treatment of Low Back Pain: Evidence, Challenges, and Promising Directions

The Chiro.Org Blog


SOURCE:   Lancet. 2018 (Mar 20) [Epub]


Nadine E Foster, Johannes R Anema, Dan Cherkin, Roger Chou, Steven P Cohen, Douglas P Gross, Paulo H Ferreira, Julie M Fritz, Bart W Koes, Wilco Peul, Judith A Turner, Chris G Maher, on behalf of the Lancet Low Back Pain Series Working Group

Arthritis Research UK Primary Care Centre,
Research Institute for Primary Care and Health Sciences,
Keele University,
Staffordshire, UK.


Many clinical practice guidelines recommend similar approaches for the assessment and management of low back pain. Recommendations include use of a biopsychosocial framework to guide management with initial non-pharmacological treatment, including education that supports self-management and resumption of normal activities and exercise, and psychological programmes for those with persistent symptoms. Guidelines recommend prudent use of medication, imaging, and surgery. The recommendations are based on trials almost exclusively from high-income countries, focused mainly on treatments rather than on prevention, with limited data for cost-effectiveness. However, globally, gaps between evidence and practice exist, with limited use of recommended first-line treatments and inappropriately high use of imaging, rest, opioids, spinal injections, and surgery. Doing more of the same will not reduce back-related disability or its long-term consequences.

This is just one article from a series of 4:

The Lancet 2018 Series on Low Back Pain

The advances with the greatest potential are arguably those that align practice with the evidence, reduce the focus on spinal abnormalities, and ensure promotion of activity and function, including work participation. We have identified effective, promising, or emerging solutions that could offer new directions, but that need greater attention and further research to determine if they are appropriate for large-scale implementation.

These potential solutions include focused strategies to implement best practice, the redesign of clinical pathways, integrated health and occupational interventions to reduce work disability, changes in compensation and disability claims policies, and public health and prevention strategies.


From the FULL TEXT Article:

Introduction

Despite the plethora of treatments and health-care resources devoted to low back pain, back-related disability and population burden have increased. [1, 2] The first paper [3] in this Series describes the global burden and effect of low back pain and provides an overview of the causes and course of low back pain. In this Series paper, we summarise the evidence for effectiveness of interventions for the prevention and treatment of low back pain and the recommendations from best practice guidelines. Despite generally consistent guideline recommendations around the world, clear evidence exists of substantial gaps between evidence and practice that are pervasive in low-income, middle-income, and high-income countries. Different response strategies are needed that prevent and minimise disability and promote participation in physical and social activities. Here we highlight examples of effective, promising, or emerging solutions from around the world and make recommendations to strengthen the vidence base for them.


Prevention


Table 1

By contrast with the large number of trials that assess treatments for low back pain, evidence about prevention, particularly primary prevention, is inadequate (table 1). Most of the widely promoted interventions to prevent low back pain (eg, work-place education, no-lift policies, ergonomic furniture, mattresses, back belts, lifting devices) do not have a firm evidence base. A 2016 systematic review [4] identified only 21 trials with 30,850 adults (one in a low-middle-income country [Thailand]), and a 2014 systematic review [5] analysed only 11 randomised controlled trials with 2,700 children (one in a low-middle income country [Brazil]).

There are more articles like this @ our:

Low Back Pain and Chiropractic Page

(more…)