

Support Chiropractic Research!

Frank M. Painter

About Frank M. Painter

I was introduced to Chiro.Org in early 1996, where my friend Joe Garolis helped me learn HTML, the "mark-up language" for websites. We have been fortunate that journals like JMPT have given us permission to reproduce some early important articles in Full-Text format. Maintaining the Org website has been, and remains, my favorite hobby.

Sleep Characteristics in Patients with Whiplash-Associated Disorders: A Descriptive Study

By |January 7, 2014|Chiropractic Care, Whiplash|

Sleep Characteristics in Patients with Whiplash-Associated Disorders: A Descriptive Study

The Chiro.Org Blog


SOURCE:   Topics in Integrative Health Care 2012 (Dec 31); 3 (4)


Jay Greenstein, DC, CCSP, CGFI-L, CKTP, FMS; Barton Bishop, DPT, SCS, CKTI, TPI, CGFI-MP, CSCS; Jean Edward, RN, BSN; Allen Huffman, DC, CKTP, BS; Danielle Davis; Robert Topp, RN, PhD


Study Objectives:   The purpose of this study was to explore sleep habits and characteristics of patients with whiplash-associated disorders (WAD) presenting at an outpatient, chiropractic clinic using the Medical Outcomes Study (MOS) Sleep Scale.

Methods:   Fifty-one patients from an outpatient chiropractic and physical therapy clinic specializing in spinal rehabilitation participated in this cross-sectional, descriptive study. Data were collected using a descriptive survey, the Visual Analog Scale (VAS), the Neck Disability Index (NDI), and the self-administered 12-item MOS Sleep Scale. Data analysis included descriptive statistics to describe pain, disability, and sleep characteristics of the study sample, and computation of confidence intervals to determine differences in means of sleep characteristics between the non-WAD population (as determined by previous studies) and the study sample of WAD patients.

Results:   Results indicate that when compared to normative values of the non-WAD population, the sample of WAD patients in this study presents with significantly greater measures of neck disability (NDI), neck pain (VAS), sleep disturbance, snoring, shortness of breath and headache, sleep somnolence and sleep problems index I and II. This sample also presents with significantly lower measures of optimal sleep when compared to the general population.

Conclusion:   Consistent with previous research, findings from this study indicate that WAD patients have increased neck disability and pain, and poorer sleep outcomes, indicating the need for clinicians to assess sleep characteristics and incorporate interventions aimed at alleviating these symptoms when planning rehabilitation. Findings provide evidence for the need to further explore sleep disturbances among WAD patients to establish a stronger understanding of the course and prognosis of this condition.


From the FULL TEXT Article:

Introduction

Neck pain related to whiplash-associated disorders (WAD) constitutes a significant health issue that leads patients to seek medical care in chiropractic and other physical therapy, rehabilitative clinics. Studies have indicated that individuals experience multiple clinical manifestations of WADs that lead to chronicity including postural changes, disability, headache, fatigue, and sleep disturbances. [1-4] Although studies have shown that sleep disturbances occur as a result of chronic pain, few studies have explored the relationship between patients with WAD and sleep quality. [4-6]

There are many more articles like this @ our:

The Whiplash Page and the
Chronic Neck Pain and Chiropractic Page

(more…)

Epidural Steroid Injections: Are long-term Risks Worth Short Term Benefits?

By |January 5, 2014|Iatrogenic Injury, Steroids|

Epidural Steroid Injections: Are long-term Risks Worth Short Term Benefits?

The Chiro.Org Blog


SOURCE:   ACA News ~ February 2014

By William Morgan, DC


Outpatient procedures are where the money is in medicine these days. Such procedures are invasive treatments that are not quite surgery but are not conservative care either. Non-surgical procedura lists are falling over themselves at an alarming rate to learn these lucrative businesses. This is true in several medical specialties: cardiac catheterization labs, GI endoscopies and colonoscopies, interventional radiology procedures, PMR pain procedures, urologic cystoscopies, chiropractic manipulation under anesthesia, epidural steroid injection therapies and many other pain procedures. If utilized correctly, these procedures may be valuable tools in the treatment of patients by preventing more invasive procedures, and in the case of cystoscopies and colonoscopies, aid in the early detection of cancer.

These procedures can be done quickly with assembly line efficiency and are very profitable for the physicians. In the case of epidural steroid injections (ESI), a ten-minute epidural procedure will generally yield anywhere from a couple hundred to a couple thousand dollars, though I have heard of a series of three epidurals going for as much as $8,000. Furthermore, if done in an outpatient facility, the physician does not have to split the fees with a hospital, and the insurance company does not need to pay the higher costs that normally accompany hospital-based procedures. Last year in the United States, the Centers for Medicare and Medicaid Services (CMS) paid for nearly nine million ESI. This number may not appear surprising at first, but when you consider that ESI therapies are neither approved by the FDA [1] nor recommended by the manufacturers [2] due to reports of severe adverse events, it becomes alarmingly relevant. Note that the CMS number is not the total number of ESI performed in the United States. The nine million number represents only those ESI paid for by CMS. When we add in the number of ESI performed in the DOD, VA, workers’ compensation systems and private insurance, that number could conceivably be in the tens of millions.

While it is true that ESI are not FDA approved, Medicare, Medicaid, workers’ compensation and most other insurers continue to pay hundreds of millions of dollars per year for this controversial procedure.

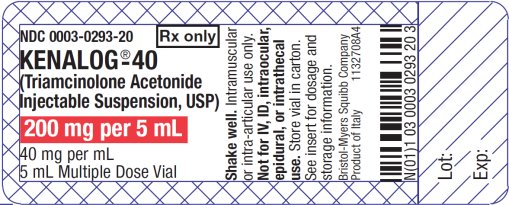
Ironically, on every vial of Kenalog (a popular steroid used for epidural injections) there is actually a warning against its use for epidural injections, yet proceduralists continue to use it.

There are more articles like this @ our:

The Iatrogenic Injury Page

(more…)

A Randomised Controlled Trial of Preventive Spinal Manipulation with and without a Home Exercise Program for Patients with Chronic Neck Pain

By |December 25, 2013|Chiropractic Care, Chronic Pain, Evidence-based Medicine|

A Randomised Controlled Trial of Preventive Spinal Manipulation with and without a Home Exercise Program for Patients with Chronic Neck Pain

The Chiro.Org Blog


SOURCE:   BMC Musculoskelet Disord. 2011 (Feb 8);   12:   41


Johanne Martel, Claude Dugas, Jean-Daniel Dubois, and Martin Descarreaux

Département de Chiropratique,
Université du Québec à Trois-Rivières,
Trois-Rivières G9A 5H7, Canada.


Background:   Evidence indicates that supervised home exercises, combined or not with manual therapy, can be beneficial for patients with non-specific chronic neck pain (NCNP). The objective of the study is to investigate the efficacy of preventive spinal manipulative therapy (SMT) compared to a no treatment group in NCNP patients. Another objective is to assess the efficacy of SMT with and without a home exercise program.

Methods:   Ninety-eight patients underwent a short symptomatic phase of treatment before being randomly allocated to either an attention-group (n = 29), a SMT group (n = 36) or a SMT + exercise group (n = 33). The preventive phase of treatment, which lasted for 10 months, consisted of meeting with a chiropractor every two months to evaluate and discuss symptoms (attention-control group), 1 monthly SMT session (SMT group) or 1 monthly SMT session combined with a home exercise program (SMT + exercise group). The primary and secondary outcome measures were represented by scores on a 10-cm visual analog scale (VAS), active cervical ranges of motion (cROM), the neck disability index (NDI) and the Bournemouth questionnaire (BQ). Exploratory outcome measures were scored on the Fear-avoidance Behaviour Questionnaire (FABQ) and the SF-12 Questionnaire.

Results:   Our results show that, in the preventive phase of the trial, all 3 groups showed primary and secondary outcomes scores similar to those obtain following the non-randomised, symptomatic phase. No group difference was observed for the primary, secondary and exploratory variables. Significant improvements in FABQ scores were noted in all groups during the preventive phase of the trial. However, no significant change in health related quality of life (HRQL) was associated with the preventive phase.

There are more articles like this @ our:

Chronic Neck Pain and Chiropractic Page and our

Maintenance Care, Wellness and Chiropractic Page

(more…)

Chiropractors as Primary Spine Care Providers: Precedents and Essential Measures

By |December 16, 2013|Health Care Reform, Primary Care|

Chiropractors as Primary Spine Care Providers: Precedents and Essential Measures

The Chiro.Org Blog


SOURCE:   J Can Chiropr Assoc. 2013 (Dec); 57 (4): 285–291


W. Mark Erwin, DC, PhD, A. Pauliina Korpela, BSc, and Robert C. Jones, DC APC

Assistant Professor, Divisions of Orthopaedic and Neurological Surgery, University of Toronto, Toronto Western Hospital, Scientist, Toronto Western Research Institute ; Associate Professor, Research, Canadian Memorial Chiropractic College.


Chiropractors have the potential to address a substantial portion of spinal disorders; however the utilization rate of chiropractic services has remained low and largely unchanged for decades. Other health care professions such as podiatry/chiropody, physiotherapy and naturopathy have successfully gained public and professional trust, increases in scope of practice and distinct niche positions within mainstream health care. Due to the overwhelming burden of spine care upon the health care system, the establishment of a ‘primary spine care provider’ may be a worthwhile niche position to create for society’s needs. Chiropractors could fulfill this role, but not without first reviewing and improving its approach to the management of spinal disorders. Such changes have already been achieved by the chiropractic profession in Switzerland, Denmark, and New Mexico, whose examples may serve as important templates for renewal here in Canada.

Keywords: primary care, spine, chiropractor


Introduction:

Between 1999 and 2008 the mean inflationary adjusted costs for ambulatory neck and/or back pain in the United States increased by a factor of 95%. [1] According to the study by Davis et al the largest proportion of increased costs are associated with specialty visits rather than primary consultations, clearly indicating that spine care places a tremendous burden upon the health care system. [1] Davis et al make recommendations with respect to cost containment for spine-related disorders which are similar to those put forth by Maniadakis and Gray ten years ago; and many of these revolve around reducing the reliance on specialty management. [2] A number of professionals with diverse backgrounds (chiropractors, massage therapists, physical therapists, osteopaths, and physicians) care for spinal pain patients. However unlike some other health care professions that have focused upon the management of condition-specific maladies, no one group has chosen to do so for certain aspects of the spine patient. Perhaps lessons learned from other condition-specific professions such as optometry and podiatry could provide important guidance in this regard.


Precedents for Professional Growth and Development:

You may also enjoy our new

Primary Care and Chiropractic Page

(more…)

A Review of the Beneficial and Harmful Effects of Laughter

By |December 14, 2013|Humor, Iatrogenic Injury, Laughter|

A Review of the Beneficial and Harmful Effects of Laughter

The Chiro.Org Blog


SOURCE:   British Medical Journal 2013 (Dec 13); 347: f7274


R E Ferner, honorary professor of clinical pharmacology [12],
J K Aronson, fellow [3]


Research

Christmas 2013: Food For Thought

Laughter and MIRTH (Methodical Investigation of Risibility, Therapeutic and Harmful): Narrative Synthesis

Every December, the BMJ publishes hilarious Christmas research.

Their 2013 offerings are now online at:

http://www.bmj.com/research


A big Thanks to Anne Taylor-Vaisey


Objective   To review the beneficial and harmful effects of laughter.

Design   Narrative synthesis.

Data sources and review methods   We searched Medline (1946 to June 2013) and Embase (1974 to June 2013) for reports of benefits or harms from laughter in humans, and counted the number of papers in each category.

Results   Benefits of laughter include reduced anger, anxiety, depression, and stress; reduced tension (psychological and cardiovascular); increased pain threshold; reduced risk of myocardial infarction (presumably requiring hearty laughter); improved lung function; increased energy expenditure; and reduced blood glucose concentration.

However, laughter is no joke — dangers include syncope, cardiac and oesophageal rupture, and protrusion of abdominal hernias (from side splitting laughter or laughing fit to burst), asthma attacks, interlobular emphysema, cataplexy, headaches, jaw dislocation, and stress incontinence (from laughing like a drain). Infectious laughter can disseminate real infection, which is potentially preventable by laughing up your sleeve. As a side effect of our search for side effects, we also list pathological causes of laughter, among them epilepsy (gelastic seizures), cerebral tumours, Angelman’s syndrome, strokes, multiple sclerosis, and amyotrophic lateral sclerosis or motor neuron disease.

Conclusions   Laughter is not purely beneficial. The harms it can cause are immediate and dose related, the risks being highest for Homeric (uncontrollable) laughter. The benefit-harm balance is probably favourable. It remains to be seen whether sick jokes make you ill or jokes in bad taste cause dysgeusia, and whether our views on comedians stand up to further scrutiny.


Introduction

“Mirth . . . prorogues life, whets the wit, makes the body young, lively, and fit for any manner of employment.”— Robert Burton, The Anatomy of Melancholy (1621)

The BMJ has not dealt seriously with laughter since 1899, when an editorialist, following an Italian correspondent’s suggestion that telling jokes could treat bronchitis, proposed the term “gelototherapy” (in Greek gelōs means laughter; in Italian gelato means ice cream). [1] The journal had, a year before, described heart failure following prolonged laughter in a 13 year old girl. [2]


(more…)

The Coming Changes in Health Care: What DCs Need to Know

By |December 12, 2013|Health Care Reform|

The Coming Changes in Health Care: What DCs Need to Know

The Chiro.Org Blog


SOURCE:   Health Insights Today


Interview with Gerard Clum, DC

by Daniel Redwood, DC


Gerard W. Clum, DC, was the first president of Life Chiropractic College West, holding office from January 1981 through January 2011. Dr. Clum has served on the board of directors or as an officer of the Association of Chiropractic Colleges (ACC), the Council on Chiropractic Education (CCE), the International Chiropractors Association (ICA), the Foundation for Chiropractic Progress (F4CP), the Chiropractic Summit and the World Federation of Chiropractic (WFC).

He is now Presidential Liaison for External Affairs at Life University and director of The Octagon, a think-tank sponsored by Life University. In addition, he serves as a consultant and expert witness in matters related to chiropractic practice/care. He has been recognized as “Chiropractor of the Year” by ICA, “Man of the Year” by Dynamic Chiropractic and as one of the top five leaders of the chiropractic profession in a Dynamic Chiropractic readers’ poll. He has lectured throughout the world and has been recognized and honored for his efforts over the years by international, national, state and local groups. He can be reached at gerrycdc@aol.com.

In recent years, Dr. Clum has spoken to numerous employer, insurance and health industry groups on behalf of the Foundation for Chiropractic Progress, providing powerful, fact-based presentations on the positive effects chiropractic inclusion can bring to both new and traditional forms of health care delivery. He is among the most knowledgeable people in the profession on issues related to the Affordable Care Act and the potential for chiropractic participation in the new entities (Patient Centered Medical Homes and Accountable Care Organizations) being developed as part of health reform.


What recent trends and changes in the health care landscape are most likely to affect present and future chiropractors?

The most immediate changes that are underway involve the refinement of the rules and regulations associated with the implementation of the Affordable Care Act. The roles of Congress and the president are complete, to some degree. Once the legislation is passed and signed, it’s turned over to the Department of Health and Human Services (HHS) or other government agencies, to begin the process of implementing the legislation. And as we all know, sometimes things get implemented differently than they were conceived by the legislators who passed them.


(more…)